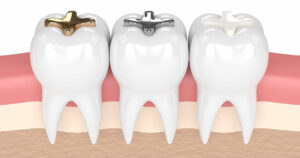
There is no single “best” type of cavity filling for every tooth. The right material depends on the size and location of the cavity, how much biting force the tooth carries, how much healthy tooth structure remains, appearance preferences, moisture control, cost, and your dentist’s clinical assessment. Common restorative materials include dental amalgam, resin composite, glass ionomer, and indirect restorations such as ceramic or gold inlays and onlays.
Important: Filling prices and lifespans cannot be predicted from material alone. Fees vary by the tooth, number of surfaces restored, material, whether the restoration is direct or laboratory/CAD-CAM made, and any additional treatment required. Ask for a written estimate before treatment and confirm your insurance coverage directly with your plan.
The Main Types of Cavity Fillings
Some restorations are placed directly into the prepared tooth during the appointment, while others are made outside the mouth and then bonded or cemented into place. The table below focuses on practical differences rather than fixed lifespan or price claims.
| Material | Appearance | Common strengths | Important limitations | Typical use |
|---|---|---|---|---|
| Amalgam | Silver/grey | Durable, wear-resistant, performs well in load-bearing areas | Not tooth-coloured; contains mercury; not appropriate for every patient or clinical situation | Direct posterior restorations when clinically appropriate |
| Composite resin | Tooth-coloured | Bonds to tooth structure; good aesthetics; versatile | Technique and moisture control matter; can stain, wear, or fracture over time | Direct restorations in front and back teeth |
| Glass ionomer | Tooth-coloured, less translucent than enamel | Releases fluoride; useful in selected low-stress areas | Lower fracture resistance than many alternatives | Selected cervical, root-surface, paediatric, liner/base, or low-load restorations |
| Ceramic | Tooth-coloured | Excellent aesthetics; stain resistance; useful for larger indirect restorations | Usually more costly than direct fillings; can fracture depending on material, design, and bite | Indirect inlays, onlays, or other restorations |
| Gold alloy | Metallic gold | Strong, wear-resistant, long clinical history | Visible; higher laboratory/material cost; usually indirect | Selected indirect inlays/onlays and other restorations |
Need a short-term restoration while waiting for definitive treatment? See our guide to temporary tooth fillings.
Amalgam (Silver) Fillings
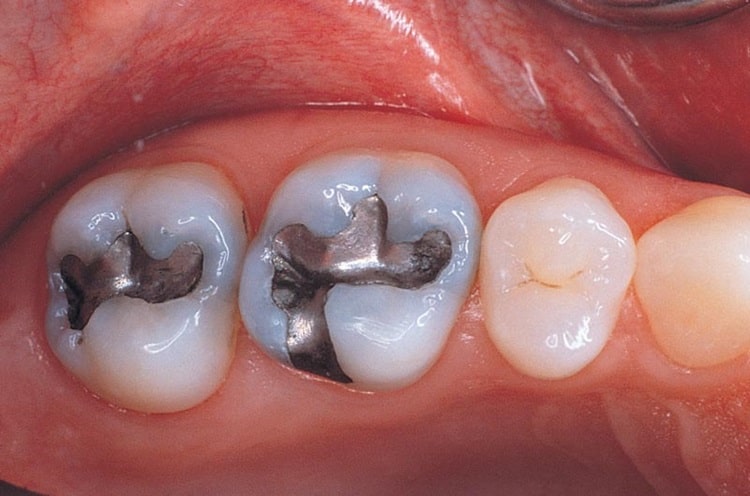
Dental amalgam is a direct restorative material with a long history of use, especially for posterior teeth that carry heavier chewing loads. Its main advantages are durability, wear resistance, and relatively straightforward placement in appropriate cases. Its main drawback is appearance because it does not match natural tooth colour.
Amalgam contains mercury combined with other metals. Health Canada states that mercury released from dental amalgam does not generally pose a health risk to the general population and does not recommend routine removal of sound amalgam fillings. Health Canada does, however, recommend specific precautions for certain patients and situations, including pregnancy, mercury hypersensitivity, impaired kidney function, and primary teeth in children when suitable alternatives are available.
Do not remove a healthy amalgam filling solely because it contains mercury without discussing the risks and benefits with a dentist. Removing an otherwise serviceable restoration also removes tooth structure and creates a new restorative procedure.
Need Help Choosing a Filling Material?
Smile Avenue Dentistry can assess the tooth, explain suitable restorative materials, and provide an estimate based on the actual treatment required. The recommended option depends on the cavity, tooth structure, bite, appearance goals, and clinical findings.
Composite (White Resin) Fillings
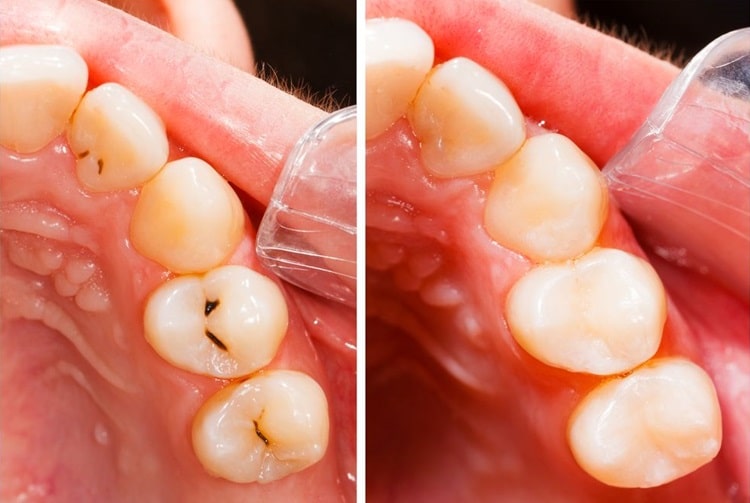
Composite resin is tooth-coloured and bonds to tooth structure, which makes it useful for both aesthetic areas and many posterior restorations. Modern composites can perform well for years when the case is suitable and the restoration is placed correctly. The ADA notes that composite longevity varies substantially and that material alone does not determine how long a restoration will last.
Composite placement is technique-sensitive. Moisture control, cavity size, tooth position, bite forces, oral hygiene, diet, and grinding or clenching can all affect long-term performance.
Composite fillings do not whiten the same way natural enamel does. If colour mismatch is a concern, read How to Whiten Fillings on Front Teeth.
Gold Restorations

Gold alloy can be used for indirect restorations such as inlays and onlays. It is strong and wear-resistant and has a long clinical history. Gold is usually more visible and more expensive than direct filling materials because laboratory or CAD-CAM fabrication and additional clinical steps may be involved.
Gold is not automatically the longest-lasting or best choice for every tooth. The design of the restoration, remaining tooth structure, bite, oral hygiene, recurrent decay risk, and patient preferences all matter.
Ceramic or Porcelain Restorations
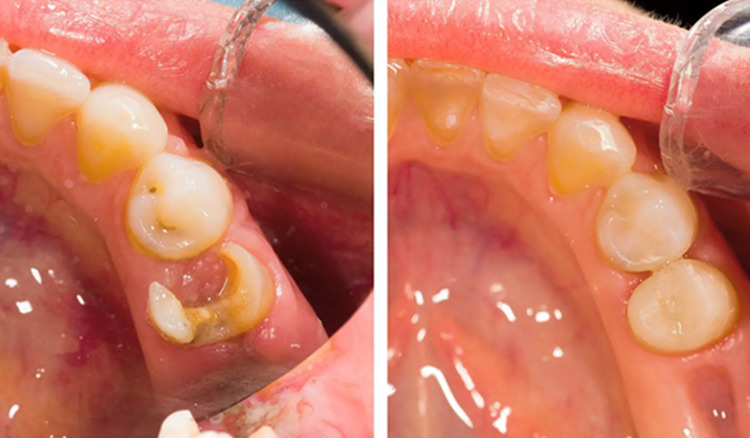
Ceramic restorations are tooth-coloured and can provide excellent aesthetics. Depending on the material and the size of the restoration, ceramic may be used for inlays, onlays, or other indirect restorations. These are often fabricated outside the mouth or with in-office CAD/CAM technology and then bonded or cemented to the tooth.
Ceramic materials differ in strength and fracture resistance, so they are not interchangeable. The dentist considers the bite, tooth position, amount of remaining tooth structure, and the specific ceramic system before recommending one.
Glass Ionomer Fillings
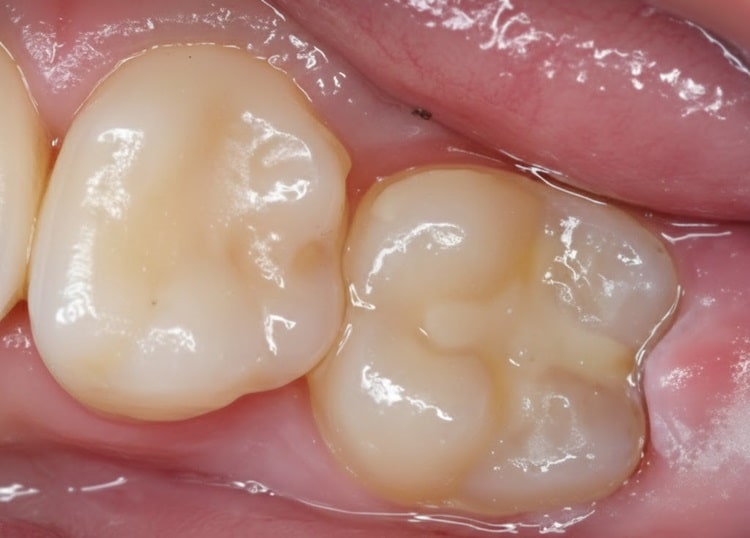
Glass ionomer is a tooth-coloured material that can release fluoride. It is generally less fracture-resistant than amalgam or composite and is commonly used in selected low-load situations, such as certain root-surface or cervical restorations, liners or bases, and some paediatric applications.
It is not accurate to say that every glass ionomer restoration lasts less than five years. Longevity varies with the specific product, location, cavity design, bite forces, moisture control, caries risk, and patient factors.
When a filling is not enough: If decay or damage reaches the pulp, root canal treatment may be considered when the tooth is restorable. If the tooth cannot be predictably restored or has a poor prognosis, tooth extraction may be considered instead. The choice depends on diagnosis and clinical findings.
What Affects the Cost of a Dental Filling in Canada?
There is no reliable Canada-wide price that applies to every cavity filling. Dental fees vary by province, clinic, tooth, restoration size, and material. Insurance plans also differ in what they reimburse.
- Number of surfaces: A larger restoration involving more tooth surfaces usually requires more work and material.
- Tooth location: Front and back teeth can require different techniques and materials.
- Material: Direct composite or amalgam and indirect ceramic or gold restorations have different clinical and laboratory requirements.
- Complexity: Deep decay, difficult access, or replacement of an old restoration can increase treatment complexity.
- Additional care: X-rays, pulp protection, sedation, root canal treatment, a crown, or other procedures are separate considerations when required.
- Insurance: Reimbursement depends on the terms, fee schedule, annual maximums, deductibles, and exclusions of the individual plan.
Ask for an estimate: Before treatment, ask the dental office for the proposed procedure and estimated fee. If you have insurance, confirm how your plan treats the recommended material and procedure rather than assuming every filling is reimbursed at the same amount.
How Dentists Choose the Right Filling Material
The choice is based on more than appearance or price. Your dentist may consider:
- the size, depth, and location of the cavity
- how much healthy tooth structure remains
- the chewing load and your bite
- whether the area can be kept dry during placement
- your risk of recurrent tooth decay
- gum position and root-surface involvement
- grinding or clenching
- aesthetic preferences
- medical or material-related considerations
- cost and insurance coverage
Children do not automatically receive glass ionomer fillings, and back teeth do not automatically require amalgam. The material should be selected for the individual tooth and clinical situation.
What to Expect During a Filling Procedure
The exact procedure varies with the material and the tooth. For a typical direct filling, the appointment may include:
- Examining the tooth and confirming that a filling is appropriate.
- Using local anaesthetic when needed to make treatment more comfortable.
- Removing decay and preparing the tooth.
- Isolating the area and placing the restorative material.
- Shaping the restoration and checking your bite.
- Finishing and polishing when appropriate.
Local anaesthetic can reduce procedural pain, but it is not accurate to promise that a filling “will not hurt at all.” Patients may feel pressure or vibration, and temporary sensitivity or soreness can occur afterward. Contact the dentist if pain is severe, worsening, persistent, or if the bite feels unusually high.
If decay is very deep and the pulp is involved, see our guide comparing tooth extraction vs. root canal treatment.
How Long Do Dental Fillings Last?
No dentist can predict an exact replacement date from material alone. Research shows wide variation in restoration survival. A filling may fail because of recurrent decay, fracture, wear, loss of retention, changes in the tooth, or other factors.
Regular dental examinations allow the dentist to monitor existing restorations. A filling should be assessed if it becomes loose, cracked, chipped, painful, sensitive, or if decay develops around it. The Canadian Dental Association notes that dentists check existing fillings and may recommend replacing restorations that are loose or broken.
Choosing a Cavity Filling in North York
If a cavity needs treatment, the goal is to restore the damaged tooth with a material appropriate for that specific situation. Composite, amalgam, glass ionomer, ceramic, and gold each have advantages and limitations. The best decision comes from balancing tooth preservation, function, appearance, cost, and long-term maintainability rather than choosing by a single lifespan or price number.
For information about restorative treatment at Smile Avenue Dentistry, visit our dental fillings in North York page.
FAQ
Does getting a dental filling hurt?
Local anaesthetic can make the procedure much more comfortable, but no treatment should be described as completely painless for every patient. You may feel pressure or vibration, and temporary sensitivity can occur afterward. Contact your dentist if pain is severe, worsening, or persistent.
Which type of cavity filling lasts the longest?
There is no single material that will last the longest in every case. Longevity depends on the material, restoration size, tooth location, bite forces, oral hygiene, decay risk, grinding or clenching, and the quality and design of the restoration.
Are amalgam fillings safe because they contain mercury?
Health Canada states that mercury from dental amalgam does not generally pose a health risk to the general population and does not recommend routine removal of sound amalgam fillings. It also recommends precautions for certain patients and situations, so discuss your medical history and material preferences with your dentist.
Will dental insurance cover every type of filling?
Not necessarily. Coverage varies by plan. Some plans reimburse one material or fee level even when another material is chosen, and deductibles, annual maximums, exclusions, or other limits may apply. Confirm the proposed procedure with your insurer.
Are white composite fillings suitable for back teeth?
Composite resin can be used successfully in many posterior teeth, but suitability depends on cavity size, bite forces, moisture control, remaining tooth structure, and other clinical factors.
When is a filling not enough to repair a cavity?
A filling may not be appropriate when too much tooth structure is missing, the tooth is badly cracked, the pulp is irreversibly damaged, or the tooth cannot be predictably restored with a direct filling. Other treatment such as an inlay, onlay, crown, root canal treatment, or extraction may be considered depending on the diagnosis.
References & Sources
- Canadian Dental Association: Fillings
- Canadian Dental Association: Tooth-Coloured Fillings
- American Dental Association: Materials for Direct Restorations
- American Dental Association: Materials for Indirect Restorations
- Health Canada: Mercury and Human Health
- Health Canada: Position Statement on Dental Amalgam